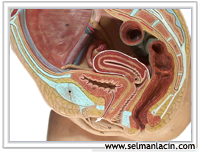
 Uterine cancer is also called endometrial cancer because it begins in the tissue covering the inner surface of the uterus, that is, the endometrium. It is actually the most common type of gynecological cancer seen in women in developed countries and can almost always be treated when caught early.
It usually occurs between the ages of 50 and 70, after menopause.
Symptoms;
Vaginal bleeding after menopause;
Heavy bleeding before menopause or bleeding between menstruations;
A pink, watery discharge from the vagina.
Obesity paves the way for endometrial cancer. It even makes treatment (surgery and radiation therapy) difficult. Nowadays, estrogen supplementation method is applied by using much lower doses of estrogen together with progesterone for a certain part of the month. Therefore, if you are on appropriate estrogen therapy, this does not put you at greater risk of cancer than the rest of the majority of the population. However, if estrogen is taken alone to combat menopause symptoms, it may cause bleeding.
Who are the women who are more likely to get uterine cancer than normal?
Those who have never given birth, those who are still menstruating at the age of 52, and those who have infertility or irregular menstrual problems. Women who have used birth control pills in the past have a lower risk of getting endometrial cancer.
How is the diagnosis made?
Uterine cancer does not show symptoms in the early stages. The PAP smear test can detect the event in less than half of the cases and it is not detected during examination. The first sign is often unexpected vaginal bleeding. If there are symptoms, the doctor performs an endometrial biopsy. In the doctor's office, he takes a small piece of the lining of the uterus for analysis, usually without the need for anesthesia. If there is uterine cancer, a biopsy will often detect it. For a more definitive diagnosis, a complete curettage is required. The doctor gently scrapes the lining of the uterus and takes tissue samples for analysis. This procedure usually requires some form of anesthesia and is usually done in a hospital, at night, at bedtime. If it is determined to be cancer and there is no reason to think that it has spread beyond the uterus, the doctor performs some tests to look for other tumors.
It is a type that usually progresses slowly and is likely not to have spread when diagnosed. This means that women who are caught can often be treated. When diagnosed early, the chance of survival for at least 5 years is 88%. Even when it spreads to surrounding tissues, this rate is 75%. In rare cases, if the tumor is a rapidly growing, lethal type, the outcome may not be so good.
treatment
* Operation;
Most doctors recommend hysterectomy (removal of the uterus). The tubes and ovaries also need to be removed because cancer has a tendency to spread to these organs as well.
* Radiation (ray) therapy;
If the cancer has spread beyond the uterus, radiation therapy must be performed after surgery. Sometimes radiation is used instead of surgery. This is a deep radiotherapy performed by inserting a device or radium into the vagina or uterus while under general anesthesia. Radium remains inside the body for several days and requires hospitalization during this time. Sometimes several methods are used together.
* Drug treatment;
If the cancer has metastasized (spread) to other parts of your body, progesterone usually stops growing. This is for 2-3 years, sometimes even longer. Other anticancer drugs may also be used.
survival
5-year survival rates for stage 1 endometrial cancer are around 90%. This rate was found to be between 69-83%, with a slight decrease in Stage 2 cases. As the stage progresses, survival decreases to around 40%. If there is a recurrence, it is most common in the first 2 years. Recurrence after 5 years is extremely rare.